Dilating Drops Are Still the Gold Standard — And Here Is Exactly Why Eye Doctors Are Not Ready to Let Them Go
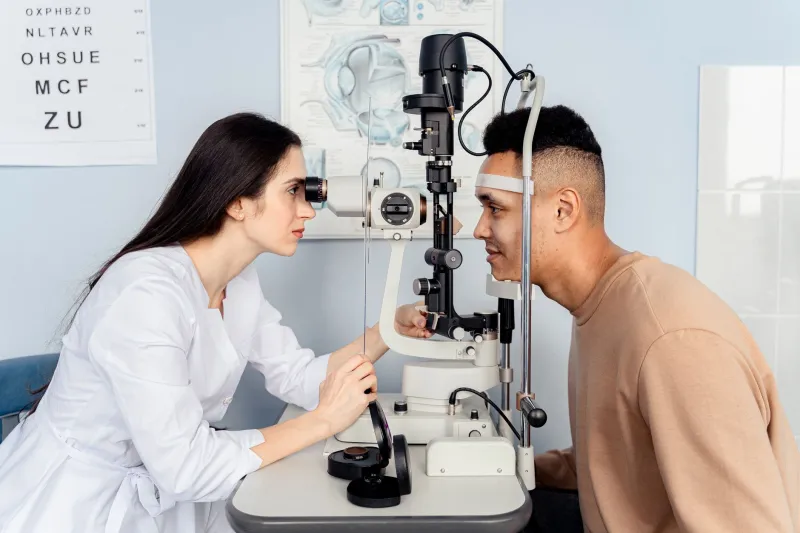
For many Americans, the dilating portion of an eye exam is the part they dread most. The blurry close-up vision. The sensitivity to sunlight that lingers for hours. The need to arrange a ride home. When patients learn that newer imaging technology exists that does not require drops, many wonder — reasonably — why their eye doctor is still reaching for that small bottle.
The answer is more nuanced than most patients expect, and understanding it may change how seriously you take this often-resisted step.
What Dilation Actually Does — And Why It Matters
Pupil dilation involves instilling pharmacological drops — typically tropicamide, phenylephrine, or a combination — into the eye. These agents temporarily paralyze the muscles that control pupil size, causing the pupil to expand from its normal two to four millimeters up to seven or eight millimeters in diameter. That widened aperture gives the clinician an unobstructed, wide-angle view of the internal structures of the eye.
Without dilation, the pupil acts like a narrow doorway. A clinician can peer through it, but the angle of view is sharply limited. The peripheral retina — the outer edges where many serious conditions first appear — becomes difficult or impossible to examine thoroughly. The optic nerve, the vitreous humor, and the far reaches of the retinal surface all come into clearer, broader view when the pupil is fully open.
This matters clinically because a number of the most consequential eye diseases begin at the periphery or in regions that are simply inaccessible through an undilated pupil. Retinal tears and detachments, for instance, frequently originate in the far peripheral retina. Diabetic retinopathy can present with changes that are only visible when the entire retinal surface is surveyed. Early-stage melanoma within the eye can hide in locations that a narrow-pupil examination cannot adequately reach.
What Modern Imaging Can — and Cannot — Replace
Widefield retinal imaging, optical coherence tomography (OCT), and ultra-widefield fundus photography have genuinely transformed eye care over the past two decades. These technologies allow clinicians to capture detailed images of the retina, the optic nerve head, and the macula without requiring pharmacological dilation in many cases.
For routine screening in lower-risk patients, these tools offer a meaningful advantage. They reduce patient discomfort, eliminate the need for a driver, and produce permanent photographic records that can be compared year over year. Several large optometric chains now offer retinal imaging as a paid add-on to standard exams, and the images they produce are clinically valuable.
However, eye care professionals are careful to draw a distinction between imaging and examination. Photographs, however high-resolution, capture a moment in time from a fixed angle. They cannot replicate the dynamic, three-dimensional assessment that a clinician performs when looking through a slit lamp with a dilating lens, adjusting the angle of view in real time, assessing the consistency of the vitreous, or evaluating subtle color variations across the retinal surface.
OCT, while extraordinary at cross-sectioning retinal layers, is most effective when the examiner already knows where to look. It is a targeted tool, not a comprehensive survey instrument. Widefield imaging, meanwhile, still has resolution limitations at the far periphery — precisely where certain pathologies prefer to hide.
Perhaps most importantly, no imaging modality currently available fully replaces the clinical judgment of a trained professional examining the eye directly. The drops, in that sense, are not a delivery mechanism for an outdated ritual. They are a means of access.
The Patients Who Need Dilation Most
Clinical guidelines from the American Optometric Association and the American Academy of Ophthalmology identify several patient populations for whom dilation is particularly important. These include individuals with diabetes, those with a personal or family history of glaucoma, patients over the age of 60, anyone experiencing new or changing floaters or flashes of light, and individuals with high degrees of myopia — who carry an elevated risk of peripheral retinal complications.
For a healthy 28-year-old presenting for a routine prescription update, the calculus may differ from that of a 55-year-old with Type 2 diabetes and elevated intraocular pressure. Eye care professionals calibrate their recommendations based on individual risk profiles, and patients are well-served by having an honest conversation with their provider about why dilation is — or is not — being recommended for them specifically.
Common Misconceptions That Lead Patients to Decline
Two misconceptions frequently drive patient resistance to dilation. The first is the belief that modern imaging has made drops obsolete. As outlined above, this overstates what current technology can accomplish. The second is the assumption that if nothing has seemed wrong in previous years, there is nothing to find.
This second assumption is particularly worth examining. Many of the conditions that dilation helps detect — early glaucomatous changes, small retinal tears, peripheral diabetic lesions — produce no symptoms whatsoever in their early stages. Patients feel fine. Their central vision is clear. Their eye chart performance is unremarkable. And yet significant pathology can be present and progressing.
Deciding to skip dilation because you feel well is, in the clinical sense, a bit like declining a blood pressure check because you feel healthy. The value of the test lies precisely in its ability to detect what symptoms have not yet announced.
When Alternatives May Be Appropriate
None of this is to suggest that dilation is always necessary for every patient at every visit. For low-risk individuals with a recent history of normal dilated exams, a clinician may reasonably determine that high-quality widefield imaging combined with an undilated slit lamp examination provides sufficient clinical information for that particular encounter.
Some practices now use dilation on a rotating schedule — for instance, performing a full dilated exam every two to three years for lower-risk patients while using imaging technology in the intervening visits. This approach can reduce patient burden while maintaining an appropriate standard of care, provided the imaging quality is high and the clinician reviews the images thoroughly.
The key phrase is clinical judgment. The decision to dilate or not should be made by the examining provider based on your specific history, risk factors, and the quality of available imaging — not by patient preference alone or by cost considerations.
A Step Worth Tolerating
The inconvenience of pupil dilation is real. The blurred near vision, the light sensitivity, the disruption to a workday — none of these are trivial. But they are temporary, typically resolving within four to six hours, and they are the price of a genuinely comprehensive view of one of the body's most complex and irreplaceable organs.
When your eye care provider recommends dilation, the appropriate response is not to weigh it against the inconvenience of the afternoon, but to consider what might be missed if the examination is abbreviated. For most patients, that calculation resolves fairly quickly in favor of the drops.